
Cholesterol, LDL, HDL, ApoB and Lp(a): how do these markers differ?

Sonia Biecka
Dietitian

Medical review: lek. Wojciech Sierocki
Content medically reviewed by an Optimals team physician.
A basic lipid panel covers total cholesterol, LDL, HDL and triglycerides. ApoB and lipoprotein(a), or Lp(a), are also appearing more and more often in diagnostics. Although all of these markers relate to lipid metabolism, each tells you something different about the risk of developing cardiovascular disease.
Normal total cholesterol does not always mean a low risk of atherosclerosis. Likewise, a high HDL level does not guarantee protection against heart disease. What matters most is the amount of atherogenic lipoproteins, meaning particles that can take part in the development of atherosclerosis, and the presence of other risk factors.
Total cholesterol. What does it actually show?
Cholesterol is a compound the body cannot function without. It is used to build cell membranes and to synthesise steroid hormones, bile acids and vitamin D.
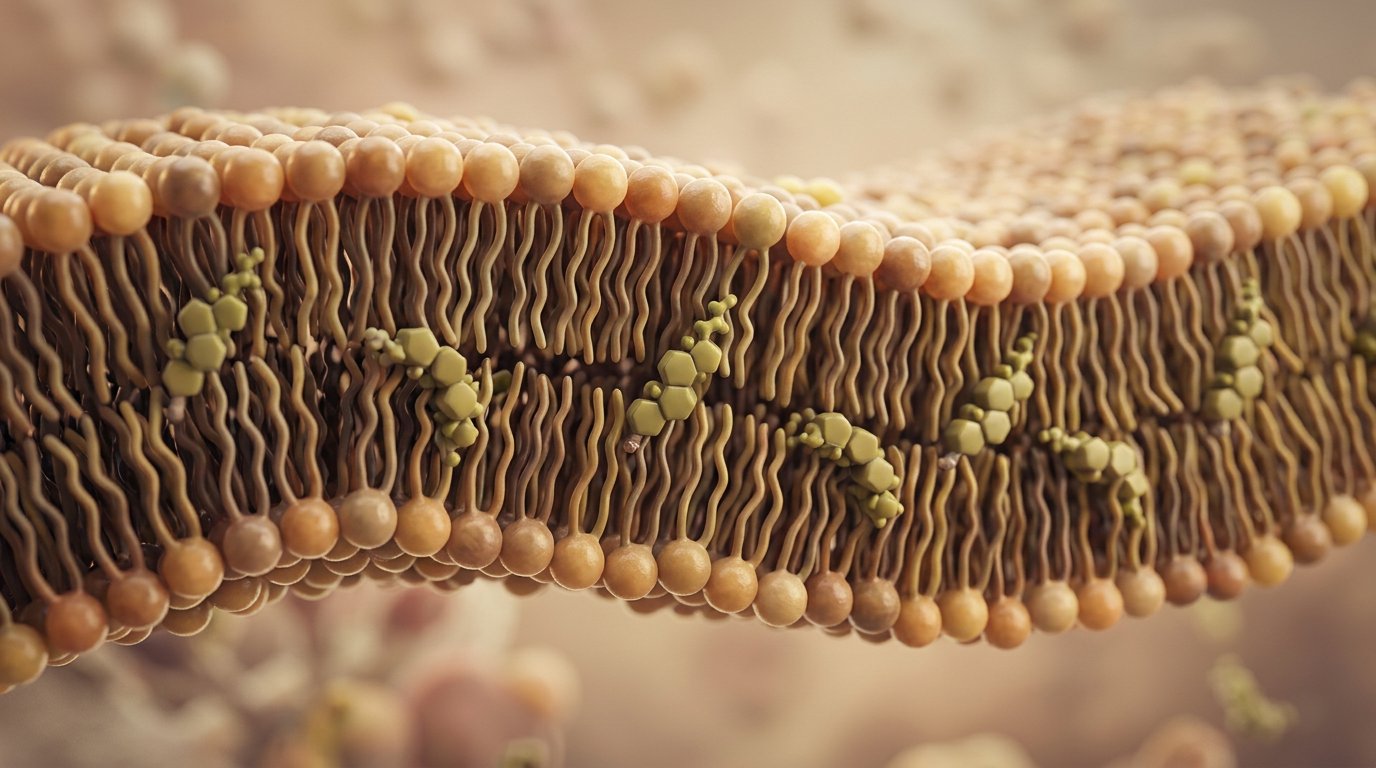
The body produces cholesterol itself, mainly in the liver, and part of it comes from food. Because cholesterol dissolves poorly in water, it is carried in the blood by lipoproteins, particles made of fats and proteins.
Total cholesterol (TC) is the combined amount of cholesterol carried by all the different lipoprotein fractions.
Its level, however, says nothing about the proportions between them. Two people with total cholesterol of 220 mg/dL can have completely different LDL and HDL levels and a different cardiovascular risk.
That is why total cholesterol on its own has limited diagnostic value. The 2024 Polish laboratory guidelines state that LDL-C and non-HDL-C are the key markers in assessing lipid disorders, with ApoB and Lp(a) also relevant in specific situations [1].
LDL. Why does its level matter so much?
LDL, or low-density lipoproteins, carry cholesterol between the liver and the tissues.
On a lab report, LDL-C refers to the amount of cholesterol carried by LDL lipoproteins and counted in that fraction by the given laboratory method.
A persistently elevated LDL-C level promotes the entry of atherogenic lipoproteins into the artery wall. Their retention triggers inflammatory processes and leads to the gradual development of atherosclerotic plaque.
Atherosclerosis can stay silent for many years while increasing the risk of heart attack, ischaemic stroke and peripheral artery disease.
The link between LDL-C and atherosclerosis has been confirmed in epidemiological, genetic and clinical studies. Lowering LDL-C reduces the risk of cardiovascular events, which is why it remains one of the core goals of prevention and treatment [2].
What LDL level is normal?
LDL-C targets depend on individual cardiovascular risk. The 2025 focused update of the European ESC/EAS guidelines kept the treatment goals set out in the 2019 guidelines [2, 3].
| Risk category | LDL-C target |
|---|---|
| Low | below 116 mg/dL |
| Moderate | below 100 mg/dL |
| High | below 70 mg/dL |
| Very high | below 55 mg/dL |
For patients at high and very high risk, an additional reduction of LDL-C by at least 50% from baseline is recommended.
The very-high-risk group includes, among others, people who have had a heart attack and patients with diagnosed atherosclerotic cardiovascular disease.
In practice, an LDL-C result of 95 mg/dL can be appropriate for one person and clearly too high for a patient after a heart attack.
The risk category depends on the whole clinical picture, including age, blood pressure, smoking, diabetes, chronic conditions and previous cardiovascular events.
HDL. Does high "good" cholesterol always protect the heart?
HDL, or high-density lipoproteins, take part in, among other things, reverse cholesterol transport from the tissues back to the liver. That is one of the reasons HDL was called "good cholesterol" for many years.
Observational studies showed a link between low HDL-C and a higher risk of cardiovascular disease. At the same time, attempts to raise HDL-C with drugs generally did not lead to the expected reduction in cardiovascular events.
Current research suggests that the functionality of HDL particles also matters, and a standard lipid panel does not assess it.
A review published in 2023 describes a relationship in which both low and very high HDL-C levels may be associated with increased health risk. The relationship differs between the populations studied and does not prove that high HDL itself causes disease [4].
High HDL-C does not offset the risk that comes from elevated LDL-C.
For example, a person with HDL-C of 80 mg/dL and LDL-C of 170 mg/dL still needs an assessment of their atherosclerosis risk.
Today HDL-C is treated mainly as a supporting marker in risk assessment rather than a treatment target in its own right.
Non-HDL. A marker you can calculate yourself
Non-HDL cholesterol covers the cholesterol carried by all the main atherogenic fractions, including LDL, VLDL, IDL and Lp(a).
It is calculated by subtracting HDL-C from total cholesterol:
Non-HDL-C = total cholesterol − HDL-C
For example, with total cholesterol of 220 mg/dL and HDL-C of 70 mg/dL, non-HDL-C is 150 mg/dL.
This marker gives broader information than LDL-C because it also includes cholesterol carried by other potentially atherogenic lipoproteins.
It is particularly useful in people with elevated triglycerides, obesity, type 2 diabetes and metabolic disorders [1, 5].
An added advantage is that it can be calculated from a basic lipid panel, without a separate test.
ApoB. Why is it increasingly recommended?
Apolipoprotein B (ApoB) is a protein found on the surface of atherogenic lipoproteins. Every LDL, VLDL, IDL and Lp(a) particle carries one molecule of ApoB100.
This means that measuring ApoB lets you estimate the number of atherogenic particles circulating in the blood, while LDL-C measures the amount of cholesterol they carry.
This difference matters a great deal clinically.
Two people can have similar LDL-C levels but a different number of LDL particles. In one person the particles may carry more cholesterol each, in the other less. In the second case, more particles are needed to carry a similar amount of cholesterol.
In such situations ApoB may point to a higher risk of atherosclerosis than LDL-C alone would suggest.
The 2024 National Lipid Association consensus confirms that ApoB can more accurately reflect the burden of atherogenic lipoproteins, especially when ApoB and LDL-C results are discordant [5].
When is it worth measuring ApoB?
The test can be especially useful in patients with type 2 diabetes, obesity, metabolic syndrome or high triglycerides, and in people on cholesterol-lowering treatment.
According to the European guidelines, the secondary ApoB treatment targets are below 100 mg/dL at moderate risk, below 80 mg/dL at high risk and below 65 mg/dL at very high cardiovascular risk [3].
ApoB complements the standard lipid panel and helps assess a patient's situation more precisely. It does not, however, replace the assessment of other risk factors.
Lp(a). A marker driven mainly by genetics
Lipoprotein(a), or Lp(a), is a particle similar to LDL that contains an additional protein called apolipoprotein(a).
An elevated level is associated with an increased risk of coronary heart disease, heart attack, ischaemic stroke and aortic valve stenosis.
Unlike many other lipid markers, the Lp(a) level is more than 90% genetically determined [2].
This means that even people with a healthy lifestyle and normal LDL-C can have elevated Lp(a).
When and how to interpret Lp(a)?
The 2025 ESC/EAS focused update recommends considering measuring lipoprotein(a) at least once in adult life. This matters especially for people with a family history of premature cardiovascular disease and suspected familial hypercholesterolaemia.
A level above 50 mg/dL, which the European guidelines treat as roughly equivalent to about 105 nmol/L, is considered a factor that increases cardiovascular risk [2].
Results may be reported in mg/dL or nmol/L. The units refer to different properties of Lp(a), so there is no single exact conversion factor that can be applied to every result.
High Lp(a) does not mean cardiovascular disease will definitely develop. It does, however, signal the need for a closer look at other risk factors, especially LDL-C, blood pressure and smoking.
Diet and physical activity have little effect on the Lp(a) level itself, but they remain important for overall cardiovascular risk. In people with high Lp(a), effective LDL-C control becomes particularly important [6].
How to read a lipid panel in practice?
Each marker provides different information, so they are best analysed together.
| Marker | What does it show? |
|---|---|
| Total cholesterol | The total amount of cholesterol in the blood |
| LDL-C | The amount of cholesterol carried by the LDL fraction |
| HDL-C | The amount of cholesterol carried by the HDL fraction |
| Non-HDL-C | The amount of cholesterol carried by the atherogenic fractions |
| ApoB | The approximate number of atherogenic lipoprotein particles |
| Lp(a) | Additional, mainly genetically determined cardiovascular risk |
The lipid panel remains the basic test, ideally including non-HDL-C. Measuring Lp(a) at least once in life can reveal an important risk factor that may go unnoticed in routine testing.
ApoB adds information especially in people with metabolic disorders or discordant lipid results.
A routine lipid panel, one of the preventive tests worth doing once a year, usually does not require fasting. In certain situations, for example with markedly elevated triglycerides, a doctor or laboratory may recommend repeating the test after fasting [1].
Can diet improve all lipid markers?
Diet mainly affects LDL-C, non-HDL-C and triglycerides, and by reducing the number of atherogenic particles it can also lower ApoB.
In the prevention and treatment of lipid disorders, limiting saturated fats and replacing them with unsaturated fats is recommended. In practice this means, among other things, choosing olive oil, nuts and fish more often instead of butter, fatty cold cuts or large amounts of full-fat cheese.
Soluble fibre, found for example in oats, barley and legumes, also matters. It can reduce the absorption of cholesterol and bile acids in the gut, supporting lower LDL-C.
The current 2026 American guidelines recommend an eating pattern based on vegetables, fruit, whole grains, legumes and nuts, with saturated fats replaced by unsaturated ones [7].
The effects of dietary changes depend on baseline lipid levels, genetics and overall health. At high cardiovascular risk, diet alone may not be enough and drug treatment becomes necessary.
Frequently asked questions
Does normal total cholesterol mean I have no cholesterol problem?
No. Normal total cholesterol can go hand in hand with elevated LDL-C, ApoB or Lp(a). An assessment requires looking at the full lipid panel and your individual cardiovascular risk.
Can high HDL offset elevated LDL?
No. High HDL-C does not remove the risk that comes from an excess of atherogenic lipoproteins. That is why high LDL-C needs to be assessed regardless of the HDL-C result.
Is it worth testing ApoB if my LDL is normal?
In some situations, yes, especially with obesity, type 2 diabetes, elevated triglycerides or increased cardiovascular risk. ApoB can reveal a higher number of atherogenic particles than the LDL-C level alone suggests.
Does Lp(a) need to be tested regularly?
Usually a measurement at least once in adult life is enough, because its level is largely genetically determined. Repeating the test may be justified in specific clinical situations.
Can you have high Lp(a) despite a healthy diet?
Yes. The Lp(a) level depends mainly on genetics. A healthy diet still matters, because it helps control other risk factors, LDL-C in particular.
Put this into practice with a doctor and a dietitian
Optimals Membership · 349 PLN/mo
Ongoing care from a doctor and a dietitian, with the app every day
References
- Solnica B, Sygitowicz G, Sitkiewicz D, et al. 2024 Guidelines of the Polish Society of Laboratory Diagnostics and the Polish Lipid Association on laboratory diagnostics of lipid metabolism disorders. Arch Med Sci. 2024;20(2):357–374. doi:10.5114/aoms/186191.
- Mach F, Koskinas KC, Roeters van Lennep JE, et al. 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J. 2025;46(42):4359–4378. doi:10.1093/eurheartj/ehaf190.
- Mach F, Baigent C, Catapano AL, et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk. Eur Heart J. 2020;41(1):111–188. doi:10.1093/eurheartj/ehz455.
- Razavi AC, Mehta A, Jain V, et al. High-Density Lipoprotein Cholesterol in Atherosclerotic Cardiovascular Disease Risk Assessment: Exploring and Explaining the U-Shaped Curve. Curr Cardiol Rep. 2023;25(12):1725–1733. doi:10.1007/s11886-023-01987-3.
- Soffer DE, Marston NA, Maki KC, et al. Role of apolipoprotein B in the clinical management of cardiovascular risk in adults: An Expert Clinical Consensus from the National Lipid Association. J Clin Lipidol. 2024;18(5):e647–e663. doi:10.1016/j.jacl.2024.08.013.
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925–3946. doi:10.1093/eurheartj/ehac361.
- Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2026;153(17). doi:10.1161/CIR.0000000000001423.